
 E-Submission
 Yeungnam University College of Medicine
Indexed in: ESCI, Scopus, PubMed,
PubMed Central, Embase, CAS, KCI
PubMed Central, Embase, CAS, KCI
FREE article processing charge

Search
- Page Path
- HOME > Search
Communications
- Psychiatry and Mental Health
- Toward proactive consultation–liaison psychiatry in Korea: a model proposed for a changing healthcare environment
-
So Hye Jo

- J Yeungnam Med Sci. 2026;43:75. Published online November 16, 2026
- DOI: https://doi.org/10.12701/jyms.2026.43.75 [Epub ahead of print]
- 124 View
- 6 Download
-
 Abstract
 PDF
- Consultation–liaison (C–L) psychiatry in general hospitals in Korea is based on referrals. Consequently, evaluations often begin only after the psychiatric, cognitive, or behavioral conditions become clinically apparent. This consultative approach is associated with the risk of failing to detect early-stage conditions that present with nonspecific or subtle symptoms such as hypoactive delirium, suicide risk, drug withdrawal, and cognitive decline. This limitation must be carefully considered, particularly in the Korean healthcare environment, where inpatient care is shared among healthcare professionals and across shift work and the demands for patient safety and quality of care are increasing. After reviewing key international evidence on proactive C–L psychiatry, a phased model applicable to general hospitals in Korea was proposed. International studies indicate that the proactive C–L psychiatry model is feasible in clinical practice and acceptable to patients and healthcare providers. The proposed model involves the identification of patients with potential psychiatric needs through complementary clinical pathways, with optional electronic medical record assistance, early risk recognition by ward staff, protocol-based secondary screening and care coordination by appropriately qualified psychiatric advanced practice nurses, targeted interventions by C–L psychiatrists, and continuous multidisciplinary feedback and follow-up management. To improve efficiency, this model should initially be piloted in high-risk wards, with subsequent expansion based on its feasibility, patient safety, healthcare provider experience, and clinical outcomes.
Original article
- Surgery
- Health system disruption and oncologic consequences: a retrospective observational study of South Korea’s 2024 medical walkout
-
Seung Ho Song, Chang Hyun Kim, Soo Yeun Park
- J Yeungnam Med Sci. 2026;43:4. Published online December 18, 2025
- DOI: https://doi.org/10.12701/jyms.2026.43.4

- 4,762 View
- 57 Download
- 1 Web of Science
- 2 Crossref
-
Abstract
PDF
 Supplementary Material
- Background
In February 2024, a sudden government policy to drastically increase medical school admissions triggered the mass resignations of medical trainees across South Korea, severely disrupting hospital operations. This study aimed to evaluate the impact of the resulting healthcare workforce disruptions on short-term clinical outcomes and the timing of colorectal cancer surgeries.
Methods
This retrospective comparative study analyzed patients with colorectal cancer treated at two national university hospitals in Daegu and Gwangju, South Korea. Patients who first visited the colorectal surgery department between March and August of 2023 and 2024 were included. Data from 2020 to 2022 were used for extended comparisons. The primary outcome was the interval from initial outpatient visit to surgery. Secondary outcomes included treatment modality distribution, tumor staging, and postoperative complications.
Results
A total of 895 patients in 2023 and 853 in 2024 were included. In 2024, only 39.5% of patients (337/853) underwent upfront surgery compared to 63.5% (569/895) in 2023. The median time to surgery increased from 30 days (interquartile range [IQR], 22–44 days) to 52 days (IQR, 30–72 days) (p=0.001). Clinical T3–4 tumors increased from 49.9% to 59.3% (p=0.018), lymph node-positive cases increased from 25.9% to 51.3% (p=0.001), and postoperative complication rates increased from 12.0% to 28.2% (p=0.001).
Conclusion
The abrupt healthcare workforce crisis in early 2024 significantly delayed colorectal cancer surgeries and was associated with worse short-term oncologic outcomes. These findings highlight the critical importance of maintaining a stable healthcare workforce to protect access to timely cancer care. -
Citations
Citations to this article as recorded by
- Vascular Anchoring Bias in a Type A Aortic Dissection Survivor: Diagnostic Delays in Acute Care Evaluation of Hepatic and Urologic Pathology
Jason Park, Michail Koutentakis, Issac Park, Emmanuel Faluade, Rodolfo J Oviedo
Cureus.2026;[Epub] CrossRef - Changes in American Society of Anesthesiologists Physical Status Distribution and Prognostic Performance During the 2024 South Korean Healthcare Crisis: A Large-Scale Retrospective Cohort Study
Chan-Sik Kim, Sang-Wook Lee
Journal of Clinical Medicine.2026; 15(11): 4261. CrossRef
- Vascular Anchoring Bias in a Type A Aortic Dissection Survivor: Diagnostic Delays in Acute Care Evaluation of Hepatic and Urologic Pathology
Case Reports
- Obstetrics, Gynecology, and Reproductive Medicine
- Successful delayed-interval delivery performed 128 days after the vaginal delivery of the first fetus in a twin pregnancy
-
Yu-Jin Koo
- Yeungnam Univ J Med. 2018;35(1):135-139. Published online June 30, 2018
- DOI: https://doi.org/10.12701/yujm.2018.35.1.135
- 12,528 View
- 93 Download
- 2 Crossref
-
Abstract
PDF
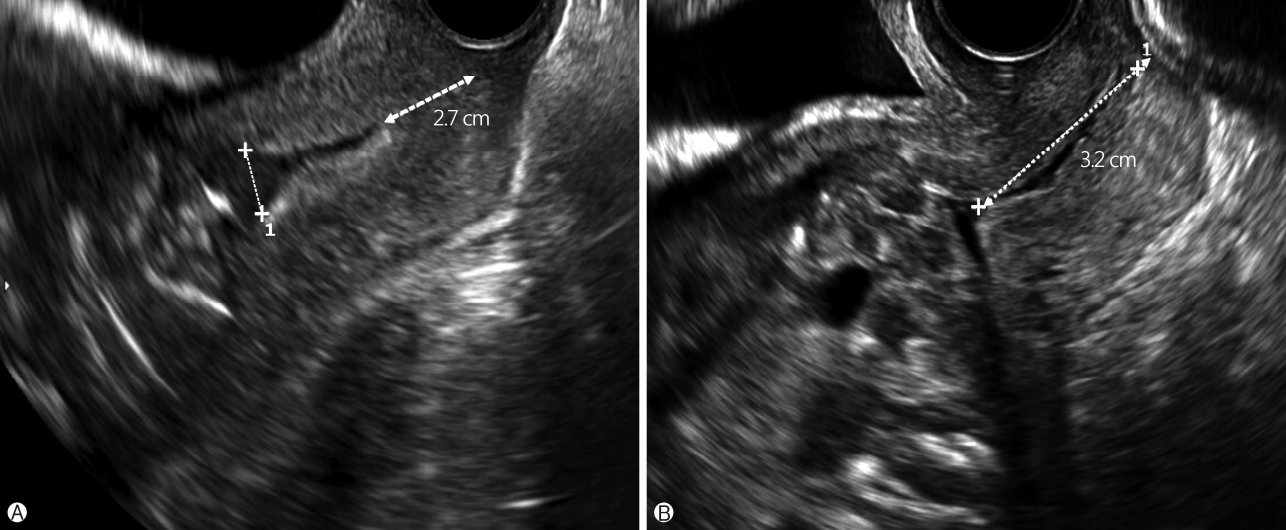
- There has been a significant increase in the number of multiple pregnancies that are associated with a high risk of preterm delivery among Korean women. However, to date, delayed-interval delivery in women with multiple pregnancy is rare. We report a case of delayed-interval delivery performed 128 days after the vaginal delivery of the first fetus in a dichorionic diamniotic twin pregnancy. The patient presented with vaginal leakage of amniotic fluid at 16 weeks of gestation and was diagnosed with a preterm premature rupture of membranes. Three days later, the first twin was delivered, but the neonate died soon after. The second twin remained in utero, and we decided to retain the fetus in utero to reduce the morbidity and mortality associated with a preterm birth. The patient was managed with antibiotics and tocolytics. Cervical cerclage was not performed. The second twin was delivered vaginally at 34 weeks and 5 days of gestation, 128 days after the delivery of the first-born fetus. This neonate was healthy and showed normal development during the 1-year follow-up period. Based on our experience with this case, we propose that delayed-interval delivery may improve perinatal survival and decrease morbidity in the second neonate in highly selected cases.
-
Citations
Citations to this article as recorded by- Cervical Cerclage at 17 Gestational Weeks for Delayed‐Interval Delivery at 15 and 27 Weeks of Gestation in a Dichorionic Twin Pregnancy: A Case Report
Motomu Suzuki, Toshiyuki Itai, Ryosuke Shindo, Nozomi Maruiwa, Sayaka Suzuki, Natsumi Ono, Azusa Tochio, Kazunori Mukaida, Soichiro Obata, Etsuko Miyagi, Shigeru Aoki
Journal of Obstetrics and Gynaecology Research.2026;[Epub] CrossRef - Delayed-Interval Delivery in a Twin Pregnancy Following Loss of One Fetus at 13 Weeks and 3 Days: A Successful Term Delivery Case Report
Su Jin Jeong, Yoonsun Kook, Bomin Kim, Seung Woo Yang, Han Sung Hwang, Han-Sung Kwon, In-Sook Sohn
Perinatology.2026; 37(3): 115. CrossRef
- Cervical Cerclage at 17 Gestational Weeks for Delayed‐Interval Delivery at 15 and 27 Weeks of Gestation in a Dichorionic Twin Pregnancy: A Case Report
- Obstetrics, Gynecology, and Reproductive Medicine
- Three cases of symphysis pubis separation associated with delivery.
- Jae Hong Ahn, Young Jin Jang, Dong Hyuk Lee, Young Gi Lee, Yoon Ki Park
- Yeungnam Univ J Med. 2000;17(1):93-98. Published online June 30, 2000
- DOI: https://doi.org/10.12701/yujm.2000.17.1.93
- 2,987 View
- 3 Download
-
Abstract
PDF
- Symphysis pubis separation is an uncommon but not rare complication of delivery. Characteristic symptoms of symphyseal separation include suprapubic pain and tenderness which radiate to the back or legs, difficult ambulation, and bladder dysfunction. Clinical history, presenting symptoms, and response to therapy are sufficient to make the diagnosis, although radiographic documentation of symphyseal separation by x-ray or ultrasound are frequently used to confirm the diagnosis. The underlying etiology of symptomatic symphyseal separation has not been fully elucidated. Associations with macrosomia, pathological joint loosening, and increased force placed on the pelvic ring have been suggested as possible etiologies. Conservative therapy, including bed rest, pelvic binders, ambulation devices, and mild analgesics usually result in complete recovery within 4-16 weeks. Our experience of three cases of peripartum symphysis pubis separation delivered from 1998 to 1999 were reviewed with related articles.
 First
 Prev




